He Clinical Logic And Selection Strategy Of Vascular Interventional Devices
Apr 10, 2026
From "Pipeline" to "Pathway": The Clinical Logic and Selection Strategy of Vascular Interventional Devices
The vascular system is the intricate and complex "lifeline pipeline network" within the human body. When any segment of this "pipeline" develops stenosis, occlusion, rupture, or abnormal dilation, performing open surgical repair from the exterior is not only highly invasive but also carries significant risks. The revolutionary nature of vascular interventional technology lies in its ability to establish a "working pathway" directly into the blood vessel through a tiny skin puncture point, only a few millimeters in size, enabling precise diagnosis and treatment of deep vascular lesions. The establishment, maintenance, and functional realization of this pathway rely entirely on a set of precisely designed, meticulously coordinated device systems, whose clinical application has formed a complete set of physical and anatomical logic. This article will analyze, from the core logic of clinical operation, the "roles," technical principles, and refined selection strategies of the key devices within this system.
1. Puncture Needle: The "Foundation Layer" and "Quality Gatekeeper" of the Pathway
Vascular puncture is the absolute starting point of the entire interventional procedure, and its quality directly determines the success and safety of all subsequent steps. Clinically, the selection of a puncture needle is by no means arbitrary; it is a comprehensive decision based on the diameter, location, pulsatility, and compressibility of the target vessel, as well as the surgical objective and the patient's vascular condition (e.g., calcification, tortuosity).
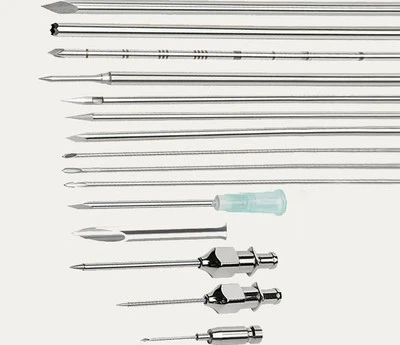
Single-Wall Puncture Needle: Relatively simple in structure, typically made from a single piece of stainless steel. Its needle tip features an optimized conical geometric design, combined with extreme sharpness achieved through nanometer-level grinding processes. This allows it to "cleanly and neatly" puncture the anterior vessel wall with minimal tissue compression and vascular wall deformation, creating a regular puncture hole. This "clean" puncture facilitates subsequent hemostasis and reduces the risk of vessel dissection. It is primarily used for arterial punctures, such as of the radial or femoral artery, especially in delicate interventions like coronary or cerebrovascular procedures where precise control of puncture depth is crucial to avoid penetrating the posterior vessel wall and causing a hematoma or arteriovenous fistula. The single-wall puncture is the standard starting point for the classic Seldinger technique (percutaneous vascular puncture technique), and its success lays the qualitative foundation for the entire pathway.
Sheathed Puncture Needle (Catheter-Over-Needle): Consists of a sharp metal stylet (needle) and a surrounding soft plastic cannula (sheath). Its core clinical advantage is that once the cannula assembly is guided into the vessel lumen by the stylet, the metal stylet can be withdrawn independently, leaving the soft plastic cannula indwelling within the vessel. This not only provides a stable, smooth, and damage-resistant protective channel for the subsequent insertion of the guidewire but, more importantly, the indwelling cannula itself can serve as a preliminary "working sheath," allowing repeated exchanges and adjustments of guidewires and catheters during the procedure without the need for repeated vessel punctures. It is particularly suitable for venous punctures (e.g., internal jugular, subclavian vein catheterization) or for handling complex situations with poor vascular access, tortuous paths, or where repeated attempts to adjust the guidewire direction are necessary. It minimizes mechanical irritation and damage to the vascular endothelium, protecting the integrity of the pathway's "portal."
2. Guidewire: The "Navigator," "Pathfinder," and "Load-Bearing Rail" of the Pathway
If the puncture needle is the "door" that opens access to the vascular world, then the guidewire is the advance scout and the "railway" for subsequent troop movement into the unknown vascular "maze." Its role extends far beyond simple "guidance."
Tip Design: The flexibility, steerability, and shape of the guidewire tip are its core safety attributes. Different designs commonly used in clinical practice, such as J-tip, straight soft tip, and shapeable tip, are tailored to different anatomical structures. For example, a J-tip automatically deflects upon encountering resistance, allowing it to safely "explore the path," conforming to the natural anatomical course of the vessel. This is especially useful for selective catheterization in tortuous vessels or at arterial ostia, effectively avoiding "blind probing" that could damage vessel branches or perforate the vessel wall.
Body Structure and Coating: The guidewire body requires segment-specific mechanical properties. The proximal section (push segment) needs sufficient support (i.e., "stiffness") to reliably advance subsequent devices like catheters and balloons to the target site. The mid-to-distal section requires excellent flexibility to navigate through angulated, tortuous vascular segments. Some guidewires are coated with a hydrophilic polymer that becomes extremely slippery upon contact with water or blood, with a very low coefficient of friction. This significantly reduces the resistance to passage through severely stenotic, calcified, or angulated lesions, serving as a key technical safeguard for crossing complex, high-risk pathologies. Furthermore, the guidewire length must be precisely selected to ensure a sufficient portion remains outside the body for manipulation, while its working length can cover the entire distance from the puncture site to the target lesion.
3. Catheter and Balloon: The "Multi-functional Workstation" and "Mechanical Pioneer" of the Pathway
The catheter is the core tool delivered to the target site along the "track" established by the guidewire. It acts as the "frontline workstation" for various intravascular operations such as angiography, measurement, drug injection, and device delivery.
Diagnostic Catheter: Its tip is pre-formed into specific geometric shapes (e.g., Judkins, Amplatz, Cobra). Each shape is designed to more efficiently and stably engage specific vascular branches (e.g., left main coronary artery, renal artery, mesenteric artery) to perform high-quality diagnostic angiography, providing a clear "roadmap" for therapeutic decision-making.
Therapeutic Catheter and Balloon: When a therapeutic catheter (e.g., guiding catheter, balloon catheter) is precisely delivered to the lesion site, true intravascular therapy begins. Taking Percutaneous Transluminal Angioplasty (PTA) as an example, the working logic of a balloon dilatation catheter involves precise force transmission and controlled deformation. The physician applies precisely controlled pressure externally via an inflator device. This pressure is transmitted without loss through the catheter lumen to the balloon located at the vascular stenosis, causing it to undergo controlled inflation. The physical expansion of the balloon exerts a sustained, radial compressive force on the stenotic vessel wall plaque, thereby fracturing or remodeling the plaque to enlarge the vessel lumen. In this process, the selection of balloon parameters-size (diameter, length), material compliance, nominal pressure, and rated burst pressure-must strictly match the anatomical parameters of the target vessel, such as reference vessel diameter, lesion length, and degree of calcification. Any mismatch can lead to complications such as under-expansion, vessel injury (dissection, rupture), or balloon rupture.
4. Stent and Filter: The "Long-term Guardian" and "Intelligent Sentinel" of the Pathway
For lesions like atherosclerotic stenosis, vessel dissection, or aneurysms, the vessel wall is highly prone to restenosis or collapse after simple balloon angioplasty due to elastic recoil, negative remodeling, or dissection propagation. In such cases, permanent or temporary endovascular implants are needed to maintain the long-term patency and structural integrity of the "lifeline pipeline."
Vascular Stent: This is a precisely engineered miniature metal mesh tubular structure, deployed and apposed to the vessel wall either via balloon expansion or self-expansion. Once implanted, its sustained radial force effectively resists vessel elastic recoil, providing a new "skeleton" for the vessel to maintain long-term luminal patency. In the treatment of aneurysms, arterial rupture, or arteriovenous fistulae, covered stents (stent-grafts) are used. These feature a layer of biocompatible polymer membrane (e.g., polytetrafluoroethylene) covering the metal framework. This membrane essentially creates a new, sealed "artificial conduit" within the vessel, directly excluding the aneurysm sac or sealing the vessel rupture, and redirecting blood flow into the normal conduit, achieving endovascular repair of complex vascular pathologies.
Vena Cava Filter (VCF): This is a specialized "intelligent mechanical trap" designed to address the risk of venous thromboembolism. It is designed to be delivered via a catheter through a jugular or femoral vein approach, accurately positioned and deployed within the target vein (typically the inferior vena cava below the level of the renal veins), expanding into an umbrella- or cone-shaped filter structure. Its core clinical logic is to intercept potentially fatal thromboemboli that have detached from deep leg veins, preventing them from traveling with venous return flow to the pulmonary arteries and causing a lethal pulmonary embolism. Concurrently, its ingenious design aims to maximize the patency of the inferior vena cava flow while intercepting clots, avoiding filter-related thrombosis. The selection of filter type (permanent, retrievable, temporary) and specific configuration requires individualized, meticulous assessment and matching with the patient's venous anatomy (diameter), thrombus burden, location, expected anticoagulation duration, and potential future retrieval needs.
Conclusion: A safe and successful vascular interventional procedure is, in essence, a meticulously orchestrated "relay race for life" performed by a sequence of devices-puncture needle, guidewire, catheter, balloon, stent/filter-working in precise coordination. Each device fulfills an irreplaceable, specific function governed by rigorous physics, material science, and anatomical/physiological principles. The process, from establishing access and navigating exploration to diagnostic assessment, mechanical therapy, and long-term support, is a tightly linked chain. Therefore, a clinician's profound understanding of the design principles, mechanical properties, indications, and limitations of each device, and the formulation of individualized device selection and operation strategies based on this understanding, is the cornerstone for ensuring procedural safety, precision, and efficiency, ultimately delivering the best clinical outcomes for the patient.