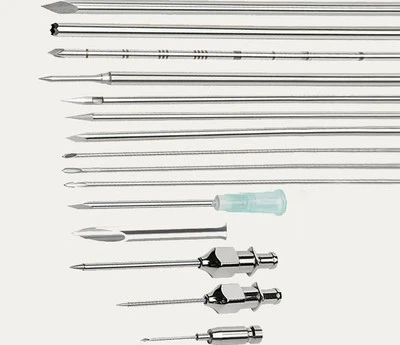
Intraosseous Needles: The Revolution Of The Hard Access in Critical Trauma Resuscitation
Apr 12, 2026
Intraosseous Needles: The Revolution of the "Hard Access" in Critical Trauma Resuscitation
Introduction: When Veins Vanish, Bone Becomes the Last Access
In the race against death during severe trauma care, establishing reliable vascular access is one of the most critical links in the resuscitation chain. However, when patients present with collapsed peripheral veins due to hemorrhagic shock or disrupted anatomy from multiple injuries, traditional intravenous (IV) puncture faces the desperate scenario of "no vein to find." At this juncture, an unconventional pathway-Intraosseous Access (IO)-leverages its unique anatomical advantage of direct access to the venous sinusoids of the bone marrow cavity, becoming a "hard access" that reverses dire situations. At the heart of this technological revolution lies the continuously evolving intraosseous puncture needle.
I. Evolution of the Puncture Needle: From "Bone Drill" to "Intelligent Tunneler"
The evolution of the modern intraosseous needle is a technological epic of miniaturization, intelligence, and precision.
First Generation: Manual Bone Needles-An Extension of Surgery
Early IO needles were essentially reinforced bone marrow biopsy needles, with operations resembling carpentry. Operators had to rely on feel and brute force to rotate and advance the needle through the hard cortical bone. This not only tested physical endurance but also carried the risk of uncontrolled depth-too shallow meant failure to enter the medullary cavity, while too deep risked damaging the opposite cortex or vital structures. Success rates hovered around 60–70%, and the average establishment time exceeded 3 minutes, proving inadequate in the time-critical environment of trauma resuscitation.
Second Generation: Mechanical Drivers-The Breakthrough of Semi-Automation
Spring-powered devices, represented by the Bone Injection Gun (BIG®), introduced the concept of "pre-stored energy." Acting like an "intraosseous nail gun," it fired the needle into the bone instantly by releasing spring tension. While this shortened operation time to about 1 minute, the non-adjustable striking force became a new problem. Excessive impact force risked bone splitting in children or osteoporotic patients, while insufficient force led to failure in young, healthy adults with dense bone.
Third Generation: Electric Drivers-The Era of Precision Control
Electric-powered systems, represented by EZ-IO® and NIO®, marked the entry of IO technology into the "intelligent era." Their core innovation lies in the closed-loop controlled rotary puncture mechanism:
Intelligent Power: A micro high-torque motor rotates the needle at 3,000–5,000 rpm. This sustained rotational shearing force penetrates the cortex more efficiently than pure axial impact.
Instant Sensing: Built-in torque sensors monitor resistance changes in real-time. The moment the needle breaches the cortex and resistance plummets, the driver stops automatically within milliseconds. This achieves self-locking at the optimal depth, perfectly solving the age-old problem of over-penetration.
Modular Needle Bodies: Dedicated needles of varying lengths (15mm–50mm) and specifications are provided for different sites (tibia, humerus, sternum). Constructed from medical-grade titanium alloy, these needles ensure strength while matching the elastic modulus of bone more closely, reducing iatrogenic fracture risk to below 0.5%.
It is this "rotary cutting + intelligent stop" mechanism that enables modern IO puncture to be completed in 20–45 seconds, with first-attempt success rates leaping to over 94%, fundamentally altering the role of IO in emergency care.
II. Anatomical Wisdom and Materials Science in Needle Design
A successful IO needle is the product of a deep dialogue between engineering and human anatomy.
Needle Tip Geometry: How to Incise Bone Elegantly
Cortical bone is not a uniform shell but a complex structure composed of compact bone and Haversian systems. Modern IO needle tips have abandoned simple pyramidal shapes for more sophisticated designs:
Tri-Cut Design: The tip features three symmetrical cutting edges, creating a "micro-drill" effect during rotation. Grooves between the edges efficiently evacuate bone debris, preventing clogging.
Tapered Transition Zone: The taper behind the tip is optimized via fluid dynamics to ensure a tight fit between the needle body and the bone tunnel post-puncture, significantly reducing the risk of extravasation (<1%).
Side Hole Fluidics: Side holes located millimeters from the tip are key to infusion efficiency. Their positions are meticulously calculated to ensure they reside in the optimal location within the vascular-rich medullary cavity, avoiding the embarrassment of "tip present, flow absent."
Material Innovation: The Triumph of Titanium Alloy
The shift from stainless steel to titanium alloy (e.g., Ti-6Al-4V ELI) is a victory for biomedical materials science. The advantages of titanium lie not just in being light and strong, but in its biocompatibility and mechanical compatibility.
Its elastic modulus (~110 GPa), while still higher than bone (<30 GPa), is closer than stainless steel (200 GPa), reducing the "stress shielding" effect and lowering the risk of microfractures around the insertion site due to uneven stress distribution.
A robust titanium oxide passivation layer forms on the surface, rendering it extremely stable in the complex biochemical environment of blood and drugs. It releases virtually no metal ions, eliminating allergic and toxic reactions.
III. Precision Guidance in Clinical Scenarios: Puncture Strategies for Different Sites
IO needles are not "one-size-fits-all." Designs and usage strategies vary significantly depending on the target anatomy.
Proximal Humerus-The High-Speed Highway
With the insertion point 1–2 cm below the deltoid tubercle, the cortex here is relatively thin, and the underlying medullary cavity connects directly to the brachial venous plexus. Needles designed for this site feature:
Moderate Length: Typically 25–30mm, sufficient to penetrate adult soft tissue and cortex.
Flow Priority: Larger inner diameters support fast infusion rates of 100–150 mL/min, meeting the high-volume demands of shock resuscitation.
Angle Adaptation: The insertion direction aims toward the contralateral shoulder joint; dedicated angle guides assist operators in precise positioning to avoid radial nerve injury.
Proximal Tibia-The Stable and Reliable Classic Pathway
Located on the flat bone surface 2–3 cm medial to the tibial tuberosity, this is the most intuitive and trainable site. Needle designs here focus on safety and universality:
Anti-Deep Insertion Design: Pediatric needles are only 15mm long and feature clear depth markings.
Skeletal Compatibility: Algorithms for push force and tip sharpness are adjustable to accommodate softer bones in children and more brittle bones in the elderly.
Quick Connection: The hub design allows for one-handed connection of infusion lines, invaluable in chaotic emergency scenes.
Sternum-The Ultimate Choice for Extreme Situations
Used only in adults, insertion occurs at the midline of the sternal body at the second intercostal level, providing the shortest path to the heart. This is the IO route closest to the heart, ensuring the fastest drug onset. Needles designed for this site represent the "pinnacle of safety art":
Mandatory Depth Limiting: Physical structures absolutely restrict puncture depth to ≤20mm, ensuring the posterior wall is not breached, preventing mediastinal injury.
Vertical Stability: Wide support bases ensure vertical insertion despite respiratory movements.
Mental Challenge: Due to proximity to the heart and great vessels, operators require rigorous training. However, its value is irreplaceable in extreme conditions like warfare or disasters where other access is impossible.
IV. Beyond the "Access": Frontier Exploration of the Needle as a Therapeutic Platform
Modern IO needles are evolving from single-function "fluid conduits" into multifunctional "therapeutic platforms."
Integrated Monitoring Functions:
Bone marrow pressure correlates well with central venous pressure. Recent studies attempt to integrate micro-pressure sensors within the needle to achieve non-invasive continuous circulatory monitoring. Furthermore, by analyzing changes in infusion resistance, indirect assessment of bone marrow edema or compartment pressure is possible, turning the needle into an early warning sentinel for compartment syndrome.
Targeted Therapy Vectors:
Bone marrow is a reservoir for many pathogens and a nest for certain tumor metastases. Researchers are exploring the direct infusion of high-concentration antibiotics or chemotherapeutics into the medullary cavity via IO needles, achieving "radical" targeted therapy. Specialized drug-eluting coated needles can sustain the release of antimicrobials during indwelling, minimizing the risk of catheter-related osteomyelitis to the extreme.
Tissue Engineering Interface:
Under the concept of controlled injury, the micro-channel created by IO puncture could become a "window" in the future. Through it, regenerative medicine products like stem cells and growth factors could be infused into the medullary cavity to promote fracture healing or treat bone marrow failure diseases, transforming the IO needle from an "emergency tool" into a "conduit for regenerative medicine."
Conclusion: Soft Power Within a Hard Access
The technological evolution of a small intraosseous needle encapsulates emergency medicine's relentless pursuit of "reliability, speed, and minimal invasiveness." Evolving from a clumsy backup plan to a core skill in Advanced Trauma Life Support (ATLS), its progress is the combined achievement of materials science, mechanical engineering, and clinical medicine.
In severe trauma care, when all soft venous accesses disappear, this "hard access," forged by wisdom, becomes the last lifeline for survival. It reminds us that the most advanced rescue technologies are often born from the most extreme demands, guarding the most fragile lives with the toughest methods. In the future, with the deeper integration of sensing, drug delivery, and biomaterials, the intraosseous needle will surely transcend its original definition as a mere "passage." It will become an intelligent hub connecting critically ill patients to precision resuscitation, integrated monitoring, and targeted therapy, building a sturdier defense line at the precipice of life.