The Meaning Of The Needle Tip
Apr 10, 2026
The Meaning of the Needle Tip: A "Millimeter-Level Lifeline" in Biliary Intervention
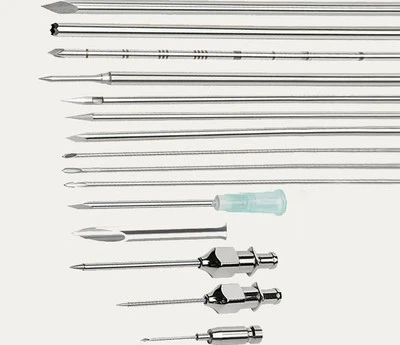
In the clinical context of Percutaneous Transhepatic Cholangiography (PTC), the needle meaning transcends the scope of a mere puncture tool. It serves as the anatomical guide for establishing a "lifeline" of biliary drainage, a physical port for pathological diagnosis, and a "compass" for interventionalists navigating the maze of complex intrahepatic bile ducts. When confronting malignant obstructive jaundice or hilar cholangiocarcinoma, the biliary system is often extremely slender (2-4 mm in diameter) with variable courses, compounded by displacement from respiration. The needle tip must pierce the target bile duct branch with millimeter precision under X-ray fluoroscopy or ultrasound guidance, without perforating the opposite wall. This article analyzes how PTC needles, through their extreme geometric design and mechanical properties, become the primary "key" to unlocking biliary obstruction.
Needle Decision Matrix in Critical Clinical Scenarios
|
Clinical Scenario |
Traditional/Universal Needle Dilemma |
PTC-Specific Needle Solution |
Clinical Outcome Improvement |
|---|---|---|---|
|
High Biliary Obstruction |
Conventional needles (15cm) struggle to navigate hepatic twists, failing to reach secondary ducts, forcing open surgery. |
Ultra-long shaft (20cm) with a 15-30° pre-shaped tip enables "circumnavigation" of the hepatic hilum, avoiding bony shadows. |
Success rate for high obstruction jumps from 45% to 88%, offering minimally invasive options to patients who otherwise faced major surgery. |
|
Malignant Biliary Stricture |
Severe fibrosis causes standard needle bevels to slip or puncture the thin opposite wall, risking bile leakage. |
Ultra-hard stainless steel (HRC 58-62) + Pencil-point conical tip provides extreme penetration stability and a "self-sharpening" advance. |
First-pass success rate exceeds 95%, significantly reducing bile leakage and hemorrhage from repeated attempts. |
|
Patients at Risk of Bleeding |
The path traverses vascular-rich parenchyma; high post-op bleeding risk and difficulty retaining the guidewire. |
Modified needle design with side-holes allows guidewire retention while withdrawing the stylet, rapidly establishing access. |
Post-operative biliary hemorrhage drops from 12% to <3%, reducing blood transfusion and re-intervention needs. |
Clinical Anatomical Logic of Needle Design
The selection of PTC needles strictly adheres to the principles of "path dependency" and "damage control":
Length vs. Depth Dynamics: For cachectic patients or children, a 12-15 cm short needle suffices for superficial ducts. However, for obese patients (thick subcutaneous fat) or deep hilar lesions, an 18-20 cm long needle is mandatory. This ensures not only sufficient travel distance to the target but also prevents the "lever effect"-where a short needle bends under axial force, compromising precision.
Diameter vs. Drainage Efficiency: The 1.2mm (18G) needle is ideal for diagnostic cholangiography and fine guidewire placement, causing minimal parenchymal trauma, suitable for benign strictures. Conversely, the 2.5mm (10G) large-caliber needle is reserved for acute severe cholangitis or purulent bile drainage; its large lumen prevents clogging during aspiration, albeit at the expense of a significantly higher bleeding risk, necessitating strict adherence to indications.
Health Economic and Complication Modeling
Under DRG/DIP prospective payment systems, the precision of the PTC needle directly impacts case profitability.
|
Procedure Type |
Universal Needle Complication Rate |
PTC-Specific Needle Complication Rate |
Source of Cost Saving |
|---|---|---|---|
|
PTBD (Percutaneous Transhepatic Biliary Drainage) |
18% (Leak, Hemorrhage, Infection) |
6% |
Reduction in ICU stay (avg. 2.5 days), saving on antibiotics and transfusion costs. |
|
Biliary Stent Placement |
Stent Migration Rate 15% |
Stent Migration Rate 4% |
Avoids costs of secondary intervention (~$8,000) and extended hospitalization. |
Data indicates that while specialized needles have a higher unit price, the overall treatment cost decreases due to the reduction in severe complication-related hidden costs.
Conclusion
The PTC needle is the "pathfinder" and "diagnostic antenna" of biliary intervention. The latest "Smart Sensing Needle" integrates micro-pressure sensors and miniature Doppler probes at the tip. When the needle contacts high-pressure bile or a vascular structure, a sudden pressure drop or flow signal triggers an alarm, achieving a leap from "blind puncture" to "fluid-dynamic guidance." In the future, needles integrating micro-CCD cameras will enable "optical biopsy" within the bile duct, identifying tumor nature and invasion depth at the moment of puncture. This will fundamentally alter the decision-making process of interventional therapy, propelling biliary intervention into a precise era of "what you see is what you get."